Adjusting Cutoffs to Optimize IPMN Surgical Decisions
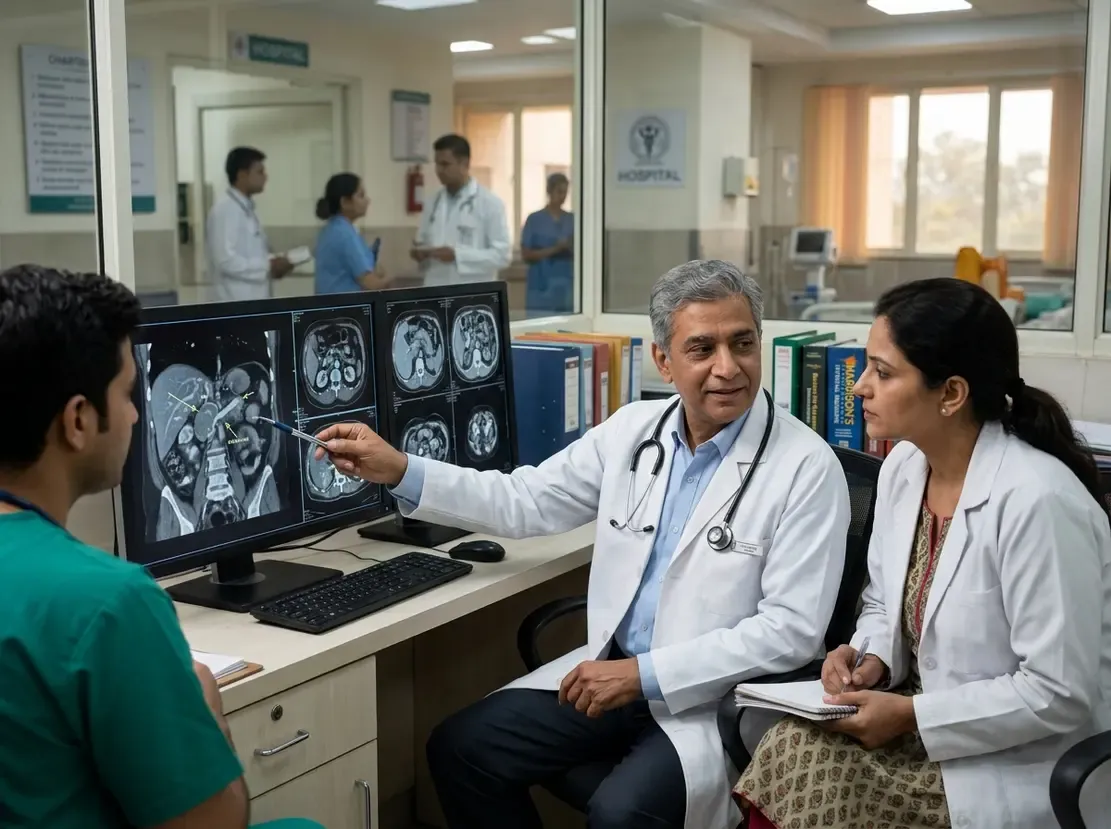
Clinicians frequently face difficult treatment choices when establishing an IPMN surgical indication. Consequently, international guidelines rely on high-risk stigmata to flag malignant transformation. However, existing criteria often yield excessive false-positive results. Therefore, patients may undergo major pancreatic surgery for non-malignant lesions. A recent retrospective study evaluated whether modifying imaging cutoffs could resolve this diagnostic dilemma.
Re-evaluating High-Risk Criteria for IPMN Surgical Indication
Currently, consensus guidelines mandate resection for obstructive jaundice, enhancing mural nodules measuring at least 5 mm, or main pancreatic duct dilation reaching 10 mm. In this study of 418 patients, obstructive jaundice and malignant cytology demonstrated exceptional specificity above 98%. In contrast, the standard cutoffs for mural nodules and duct diameter yielded a modest specificity of 80.4%. Thus, standard thresholds frequently misclassify benign mucinous neoplasms as aggressive disease. Furthermore, overall conventional high-risk stigmata showed a specificity of only 66.9%. As a result, many individuals face surgical risks without having an invasive malignancy.
Determining New Imaging Cutoffs
To overcome these limitations, researchers examined higher threshold values using receiver operating characteristic curves. Specifically, they targeted cutoffs that achieved specificities of 85%, 90%, and 95%. For enhancing mural nodules, the corresponding cutoffs rose to 9.5 mm, 12.0 mm, and 17.5 mm. Similarly, main pancreatic duct thresholds increased to 11.0 mm, 12.0 mm, and 13.5 mm. Consequently, the revised models improved the diagnostic area under the curve from 0.771 up to 0.808. However, higher specificity inevitably reduced diagnostic sensitivity. For instance, optimism-corrected sensitivity dropped from 74.4% in the 85% specificity model down to 53.1% in the 95% model.
Clinical Implications for Practice
These findings offer crucial guidance for pancreatic surgery multidisciplinary teams. In routine clinical practice, clinicians must weigh the morbidity of pancreaticoduodenectomy against the risk of missed malignancy. Therefore, surgeons should not interpret borderline nodule sizes as absolute surgical imperatives. Instead, teams should tailor decision-making to patient fitness and life expectancy. Moreover, incorporating endoscopic ultrasound and multidisciplinary review remains indispensable for borderline findings.
Frequently Asked Questions
Q1: Why do conventional IPMN criteria lead to unnecessary surgeries?
Traditional thresholds prioritize sensitivity to avoid missing cancer, but modest specificity causes high false-positive rates for benign cysts.
Q2: What new cutoffs were identified for duct diameter and mural nodules?
To reach 90% specificity, researchers identified cutoffs of 12.0 mm for mural nodules and 12.0 mm for main pancreatic duct dilation.
Q3: How should clinicians apply these findings in individual care?
Clinicians should balance patient comorbidities and operative risks against individual oncologic concerns rather than using rigid cutoffs.
References
- Park J et al. Improving predictive accuracy for surgical indication of the current management guideline for intraductal papillary mucinous neoplasm of the pancreas via cutoff adjustments. Eur Radiol. 2026 Oct 08. doi: 10.1007/s00330-026-12944-3. PMID: 42848040.
- Ohtsuka T, Fernandez-Del Castillo C, Furukawa T, et al. International evidence-based Kyoto guidelines for the management of intraductal papillary mucinous neoplasm of the pancreas. Pancreatology. 2024;24(2):255-270. doi: 10.1016/j.pan.2023.12.008.
- European Study Group on Cystic Tumours of the Pancreas. European evidence-based guidelines on pancreatic cystic neoplasms. Gut. 2018;67(5):789-801. doi: 10.1136/gutjnl-2018-316027.