Can 3D MRI Morphometry Predict Severe Neck Infections?
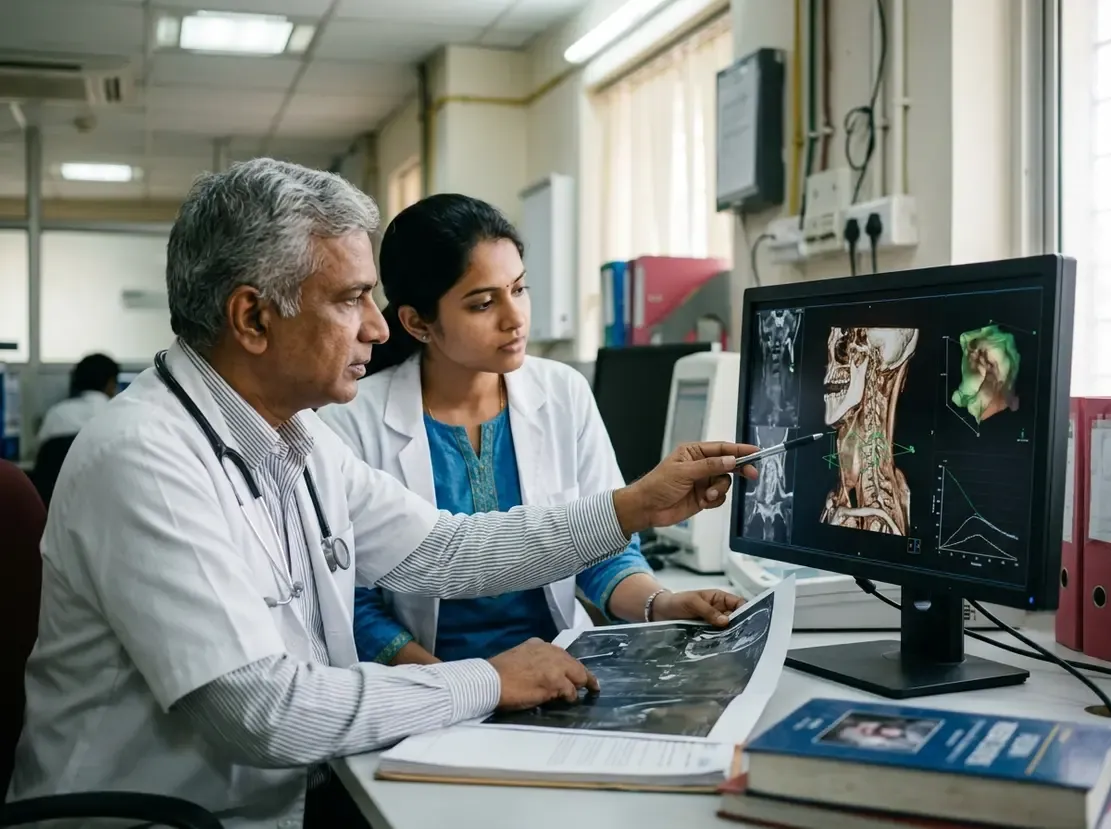
Deep neck space infections represent potentially life-threatening emergencies that require prompt risk stratification. Traditionally, clinicians assess disease severity using unidimensional abscess diameter on cross-sectional imaging. However, a single diameter measurement overlooks complex three-dimensional anatomy. Recent advances demonstrate that three-dimensional neck abscess MRI morphometry provides superior prognostic insights. Therefore, volumetric analysis captures spatial spread much better than standard linear metrics.
Beyond Unidimensional Diameter in Neck Abscess MRI
In clinical practice, deep neck abscesses rarely form simple spheres. Instead, purulent fluid tracks along complex fascial planes and anatomical spaces. Consequently, relying solely on maximum diameter can underestimate the true infectious burden.
Researchers analyzed 227 consecutive patients with surgically confirmed neck abscesses to resolve this limitation. Each patient underwent post-contrast T1-weighted imaging before surgical drainage. Experts subsequently segmented the abscess margins to extract three-dimensional morphometric parameters. These parameters included total volume, sphericity, and compactness. Furthermore, the investigators evaluated associations with intensive care unit admission and prolonged hospital stay exceeding five days.
Notably, manual segmentation achieved outstanding interobserver agreement, with intraclass correlation coefficients between 0.97 and 0.99. This finding confirms that 3D morphometric profiling provides highly reproducible anatomical measurements.
Prognostic Value of Volume and Sphericity
The investigation revealed striking differences between uncomplicated cases and severe clinical trajectories. Overall, 15% of patients required intensive care unit admission, while 18% experienced prolonged hospital stays.
Importantly, abscess volume outperformed manual diameter when predicting intensive care unit admission. Multivariable models incorporating volume achieved an area under the curve of 0.841, compared to 0.816 for manual diameter. Therefore, volumetric measurement provides superior discrimination for acute critical care triage.
Additionally, abscess geometry offered unique prognostic information regarding inpatient recovery time. Patients requiring intensive care exhibited significantly lower sphericity than stable patients. Likewise, lower sphericity strongly correlated with prolonged hospitalization. In multivariable models, adding sphericity substantially improved the prediction of prolonged stays. As a result, irregular and non-spherical abscesses signify infiltrative disease requiring protracted medical therapy.
Clinical Implications for Surgical and Critical Care
These findings carry significant relevance for head and neck surgeons, radiologists, and intensivists. In routine practice, irregular collections often dissect through multiple cervical compartments, increasing complication risks. Because standard unidimensional measurements fail to capture these complex branching geometries, clinicians may misjudge disease extent.
Furthermore, integrating quantitative morphometry into emergency imaging protocols can enhance clinical decision-making. High-risk patients presenting with large volumes or low sphericity may benefit from proactive airway management and early surgical intervention, core competencies emphasized in programs focusing on emergency medicine. Moreover, automated deep learning tools now make rapid segmentations feasible during initial radiologic reviews.
However, clinicians should note that current evidence reflects observational findings in surgically treated cohorts. Future prospective trials must confirm whether morphometry-guided clinical pathways directly improve patient morbidity and health system resource utilization.
Frequently Asked Questions
Q1: Why is 3D volume superior to unidimensional diameter in neck abscess evaluation?
Deep neck abscesses spread irregularly across fascial compartments rather than forming uniform spheres. Consequently, 3D volume captures total fluid burden much more accurately than a single linear diameter, which can be further explored through comprehensive head & neck radiology training.
Q2: What does lower abscess sphericity indicate clinically?
Lower sphericity indicates an irregular, branching fluid collection that tracks through tissue planes. Furthermore, studies show lower sphericity independently predicts prolonged hospital stay and intensive care admission.
Q3: How does MRI morphometry fit into current emergency workflows?
Post-contrast MRI provides superior soft-tissue contrast for segmenting complex neck collections. Moreover, emerging artificial intelligence algorithms enable rapid automated volumetric segmentation during acute emergency assessments.
References
- Viertonen V et al. Segmentation-based morphometric analysis of neck abscesses on MRI: associations with disease severity. Eur Radiol. 2026 Oct 08. doi: 10.1007/s00330-026-12962-1. PMID: 42848038.
- Viertonen V, Sirén A, Reima J, et al. Deep learning-based automated segmentation of neck abscesses on multiparametric MRI. Eur J Radiol. 2026;204:113165. doi:10.1016/j.ejrad.2026.113165.
- Viertonen VS, Sirén A, Nyman M, et al. Acute deep neck infection MRI: deep learning segmentation and clinical relevance of retropharyngeal edema volume. Eur Radiol Exp. 2026;10(1):15. doi:10.1186/s41747-026-00686-2.