Pancreatic Cancer Restaging: Beyond RECIST 1.1 Limits

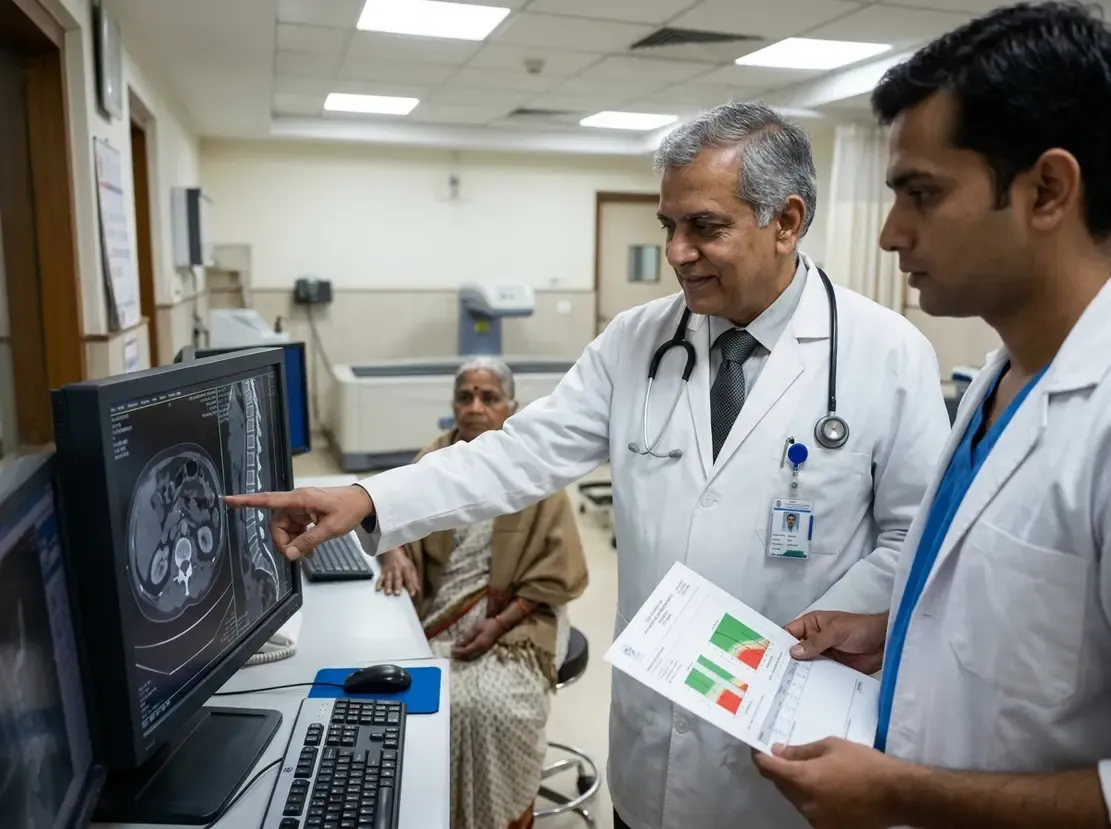
Accurate pancreatic cancer restaging after modern neoadjuvant systemic therapy represents a critical clinical dilemma. In patients with localized pancreatic ductal adenocarcinoma, multi-agent chemotherapy regimens often induce significant histological changes. Consequently, oncologists struggle to differentiate residual viable tumor from dense treatment-induced fibrosis. Standard anatomic imaging criteria frequently fail to reflect true pathological responses. Therefore, multidisciplinary teams require multimodal strategies to evaluate resectability and optimize patient outcomes.
Limitations of RECIST 1.1 in Pancreatic Cancer Restaging
Historically, clinicians relied on RECIST 1.1 criteria to evaluate treatment efficacy across solid tumors. However, these size-based metrics show profound limitations in restaging localized pancreatic ductal adenocarcinoma. Systemic therapy frequently generates profound desmoplasia, necrosis, and inflammatory fibrosis rather than immediate tumor shrinkage. As a result, tumors often retain their original dimensions on cross-sectional imaging despite substantial pathological tumor death.
Furthermore, RECIST 1.1 performs poorly when assessing stable disease and partial response. Many patients who achieve clear surgical margins remain categorized as having stable disease on imaging. Thus, relying solely on RECIST 1.1 may lead teams to incorrectly decline potentially curative surgery. In addition, persistent vascular abutment on computed tomography does not always indicate viable cancer cells. Therefore, clinicians must avoid excluding surgical exploration based exclusively on unchanging tumor size.
The Complementary Role of CT, FDG-PET, and CA19-9
To overcome anatomic imaging barriers, modern restaging protocols integrate metabolic imaging and serological biomarkers. Specifically, contrast-enhanced computed tomography remains the essential baseline foundation for defining vascular anatomy and surgical planning. Recent advances, such as dual-energy CT extracellular volume measurements, offer promising predictive value for stromal response.
Meanwhile, 18F-FDG PET/CT provides vital metabolic insights that complement structural images. A significant drop in metabolic tumor volume or maximum standardized uptake value often reflects viable tumor regression. Consequently, functional PET imaging can identify responsive patients when CT scans display stable dimensions.
Moreover, serum carbohydrate antigen 19-9 (CA19-9) kinetics serve as an invaluable surrogate for therapeutic response. A meaningful decline in post-treatment CA19-9 levels strongly correlates with improved R0 resection rates and overall survival. Nevertheless, clinicians must interpret CA19-9 with caution in Lewis antigen-negative individuals or patients with biliary obstruction. Ultimately, combining cross-sectional CT, metabolic PET imaging, and biomarker kinetics yields the most dependable restaging framework for specialists looking to deepen their expertise through a Certification Course In Clinical Oncology.
Clinical Takeaways for Surgical Selection
Accurate evaluation requires a coordinated multidisciplinary tumor board discussion. First, surgical teams should not deny resection based only on persistent radiological vascular involvement after chemotherapy. Indeed, post-treatment fibrosis frequently mimics vascular tumor invasion on restaging CT. Second, clinicians should assess biochemical response alongside functional metabolic metrics. If CA19-9 drops substantially and PET reveals metabolic response without distant metastases, exploration remains warranted. Thus, a multimodal reassessment strategy prevents unwarranted denial of curative surgical therapy in localized pancreatic cancer.
Frequently Asked Questions
Q1: Why is RECIST 1.1 inaccurate for restaging localized pancreatic cancer?
RECIST 1.1 relies exclusively on unidimensional tumor shrinkage. However, systemic therapy produces substantial desmoplastic reaction and fibrosis in pancreatic tumors. As a result, non-viable scar tissue retains mass-like dimensions, which misleads RECIST criteria into classifying successful responses as stable disease.
Q2: How does CA19-9 assist in determining surgical resectability after systemic therapy?
Serum CA19-9 kinetics offer a reliable surrogate marker for biological response. Specifically, a significant post-treatment decline in CA19-9 correlates strongly with pathological tumor regression, negative surgical margins (R0), and superior overall survival.
Q3: Should persistent vascular contact on CT preclude surgical exploration?
No, persistent vascular encasement or abutment on post-treatment CT should not automatically preclude exploration. In many patients, this persistent finding represents sterilised fibrous scar tissue rather than active viable malignancy. Therefore, patients with stable disease and falling CA19-9 levels frequently achieve successful complete resection.
For further medical insights and continuous professional development, medical practitioners can explore various Oncology Speciality Courses to stay updated with modern diagnostic and treatment protocols.
References
- Lamoré AM et al. Restaging the primary tumor in localized pancreatic ductal adenocarcinoma after systemic therapy: a scoping review of the role of CT, FDG-PET, and CA19-9. Eur Radiol. 2026 Oct 13. doi: 10.1007/s00330-026-12954-1. PMID: 42867514.
- Groot VP et al. Systematic Review and Meta-Analysis of Neoadjuvant Therapy in Pancreatic Cancer. Ann Surg Oncol. 2020;27(1):15-28.
- Tempero MA et al. Pancreatic Adenocarcinoma, Version 2.2021, NCCN Clinical Practice Guidelines in Oncology. J Natl Compr Canc Netw. 2021;19(4):439-457.