
Prostate MRI Screening: Can It Overcome PSA Pitfalls?
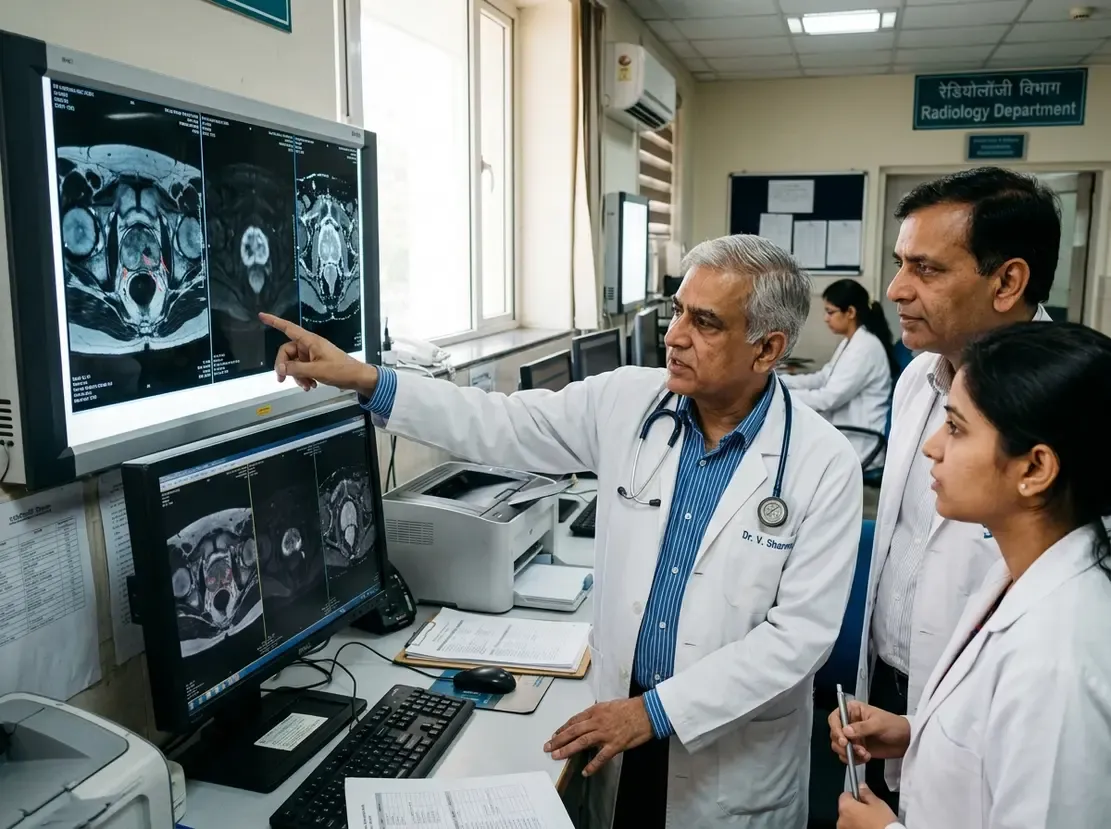
Prostate cancer remains a leading cause of oncologic morbidity worldwide. However, conventional prostate-specific antigen testing creates substantial diagnostic dilemmas. It often triggers unnecessary invasive biopsies and detects indolent tumors that never cause harm. Consequently, experts actively investigate prostate MRI screening to refine early detection pathways. A recent expert report from the ESUR Prostate MRI Working Group outlines how magnetic resonance imaging can redefine early detection. Therefore, magnetic resonance imaging provides a more balanced clinical approach by improving the detection of clinically significant disease.
Why Prostate MRI Screening Outperforms PSA Alone
Standard PSA screening reduces cancer-specific mortality, but it carries notable harms. Specifically, elevated PSA levels frequently reflect benign prostatic hyperplasia or prostatitis rather than lethal cancer. As a result, many men endure invasive biopsies with risks of infection and bleeding. Furthermore, standard biopsy schemes often detect insignificant low-grade tumors, leading to patient anxiety and overtreatment.
In contrast, magnetic resonance imaging visualizes high-grade disease with high sensitivity. Clinicians can accurately identify index lesions that warrant immediate targeted biopsy. Moreover, a negative MRI scan offers excellent reassurance due to its high negative predictive value. Thus, integrating advanced imaging prevents biopsy in men with benign conditions or insignificant lesions. Overall, the technology significantly alters the balance between screening benefits and clinical harms.
Implementation Pathways: MRI-First Versus Reflex Strategies
Healthcare systems can adopt two primary implementation approaches. First, an MRI-first pathway offers imaging to every screening participant regardless of baseline biomarkers. This approach maximizes cancer detection rates across the entire population. However, an MRI-first strategy requires immense scanner capacity and substantial financial expenditure. Most national healthcare systems lack the radiology infrastructure to sustain such high scan volumes.
Therefore, experts strongly favor a risk-stratified or reflex approach. In this pathway, clinicians perform initial risk assessments using PSA tests, clinical risk calculators, or molecular biomarkers. Only patients with elevated risk proceed to secondary imaging. Consequently, this stratified workflow concentrates advanced imaging resources on individuals who truly need evaluation. In addition, health economists report that reflex pathways offer superior cost-effectiveness and practical feasibility.
Biparametric Protocols and Future Considerations
Multiparametric MRI historically relied on intravenous gadolinium contrast for dynamic contrast-enhanced sequences. However, biparametric MRI omits contrast administration and relies solely on T2-weighted and diffusion-weighted imaging. As a result, biparametric scans reduce total acquisition time to under fifteen minutes. Furthermore, avoiding gadolinium injections lowers clinical costs, eliminates contrast-related toxicities, and improves patient comfort. Recent clinical evidence demonstrates that biparametric MRI maintains diagnostic accuracy comparable to full multiparametric scans.
Nevertheless, key operational hurdles demand attention before widespread population rollout. For instance, scanner availability remains limited in many regions, and inter-reader interpretation variability poses clinical risks. Radiology societies must establish rigorous quality assurance programs and standardized training criteria. Additionally, emerging artificial intelligence algorithms may soon assist radiologists by standardizing lesion segmentation and accelerating reporting workflows.
Frequently Asked Questions
Q1: Why is biparametric MRI preferred over multiparametric MRI for screening?
Biparametric MRI omits intravenous gadolinium contrast, which significantly shortens acquisition time and reduces operational costs. Moreover, it eliminates adverse contrast reactions while providing diagnostic accuracy equivalent to multiparametric imaging for clinically significant disease.
Q2: How does a reflex MRI screening pathway function?
In a reflex pathway, clinicians first measure PSA or evaluate clinical risk indicators before ordering imaging. Consequently, only patients with suspicious blood markers undergo MRI, preserving healthcare resources and optimizing cost-effectiveness.
Q3: Does prostate MRI eliminate the need for biopsy?
Prostate MRI does not eliminate tissue biopsy for definitive cancer diagnosis. However, it reliably rules out significant disease, allowing men with normal scans to safely avoid unnecessary tissue sampling.
References
- Brembilla G et al. Prostate cancer screening with MRI: insights from the ESUR Prostate MRI Working Group. Eur Radiol. 2026 Oct 15. doi: 10.1007/s00330-026-12863-3. PMID: 42878808.
- Kasivisvanathan V, Stabile A, Neves JB, et al. Biparametric MRI is noninferior to multiparametric MRI for prostate cancer diagnosis. JAMA. 2025;332(11):890-899.
- Hugosson J, Roobol MJ, Månsson M, et al. A 16-yr Follow-up of the European Randomized study of Screening for Prostate Cancer. Eur Urol. 2019;76(1):43-51.





